
Footlogics Insoles for Morton's Neuroma
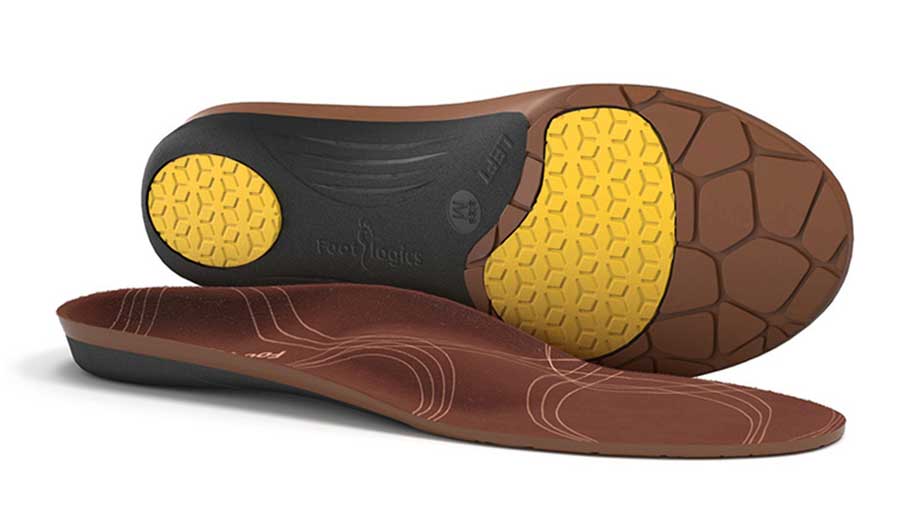
Footlogics META PREMIUM
For regular lace-up shoes, winter boots etc. Features 12mms of cushioning under the ball of the foot + firm nylon shell for added support and durability.
SHOP NOW
$49.95

Footlogics 3/4 META PRO
3/4 length premium insole for slip-on shoes. Firm nylon shell for extra support and durability.
SHOP NOW
$44.95


Insoles and orthotics for Morton's Neuroma
The right insole for Morton’s neuroma has a firm metatarsal raise sitting just behind the ball of the foot, so the bones fan out slightly and the pinched nerve between them gets more room. Cushioning alone feels nice but does not create that space.
Footlogics builds the raise into every insole in our forefoot range, together with arch support and a deep heel cup, so it lands in the same spot with every step and moves with you from shoe to shoe. Pick the model that fits the shoes you wear most, from work boots to dress flats. Every pair is podiatrist-designed and covered by our 30-day money-back guarantee.
This page is about insoles and orthotics only. For symptoms, causes and the full range of treatments, read our Morton’s neuroma guide.
How does an insole take pressure off a Morton's neuroma?
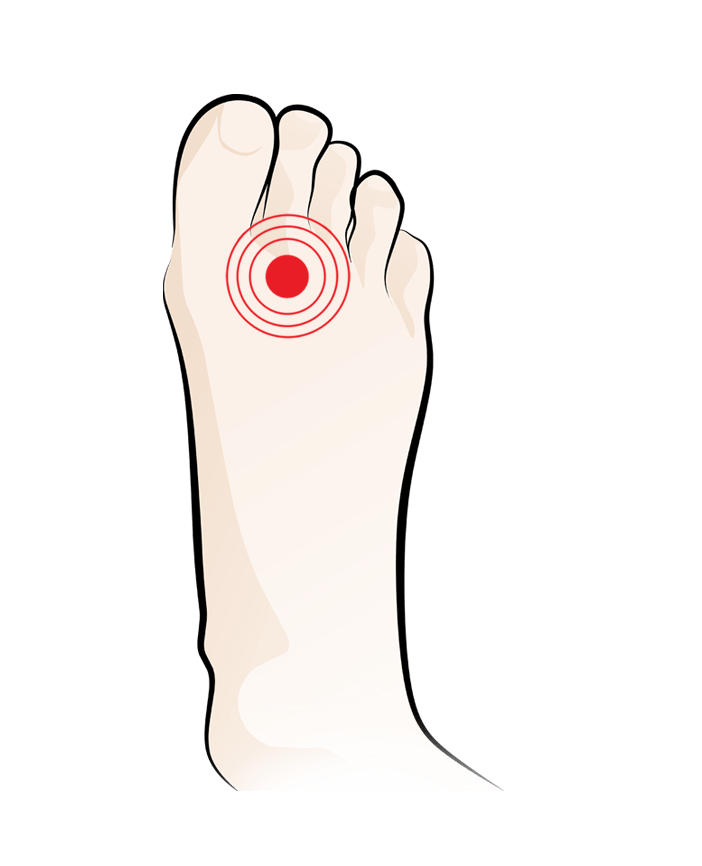
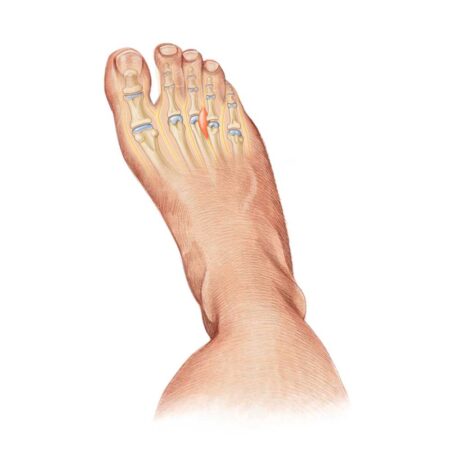
It lifts the forefoot just behind the painful spot, which spreads the metatarsal heads and gives the nerve more room. The nerve affected by Morton’s neuroma runs through a tight channel between two metatarsal heads, usually the third and fourth, underneath a band called the deep transverse metatarsal ligament. Every time your heel lifts and you push off, that channel is squeezed.
A clinical review on the NCBI StatPearls database describes a soft metatarsal pad or dome placed just behind the metatarsal heads as a way to spread them apart and ease mechanical pressure on the neuroma. An ultrasound study of 100 patients points the same way: it linked the condition to a lack of space under that ligament, and noted that narrow or high-heeled shoes close the gap further.
So an insole for Morton’s neuroma has two jobs. It needs a firm raise in the right place to open the space, and enough arch and heel support to stop the foot sliding forward off that raise. Extra padding directly under the sore spot does neither.
Is there research showing orthotics help Morton's neuroma?
Yes. The strongest evidence is a double-blind randomized trial of 72 people whose neuroma had been confirmed by MRI or ultrasound (de Oliveira et al., 2019). Half wore an insole with metatarsal and arch support; the other half wore a flat insole that looked identical. The supported group had significantly less pain when walking and better scores on several quality-of-life measures.
Older clinical studies back this up as a first step. In a staged program of 115 patients, the first stage was wider shoes plus a metatarsal pad placed behind the affected nerve. 47 patients (41%) improved enough at that stage to need no further treatment, and only 21% eventually went on to surgery (Bennett et al., 1995).
Insoles are not the fastest option, though. In a trial of 82 patients, 63% of those given footwear changes with orthoses had complete or partial relief at 12 months, against 82% of those given steroid injections (Saygi et al., 2005). Injections worked faster early on, but by one year the gap between the groups was no longer statistically significant.
Do I need an insole that corrects flat feet or over-pronation?
Not for the neuroma itself. In a small randomized trial, 23 people with Morton’s neuroma wore firm felt orthoses built either to roll their feet inward or outward. Changing the position of the foot made no significant difference to their neuroma pain (Kilmartin & Wallace, 1994).
That suggests what matters most is offloading the forefoot, not forcing the arch into a set shape. A very rigid, high-correction orthotic can even feel worse if it pushes your foot forward into the toe box.
Arch support still earns its place. A moderate arch and a deep heel cup hold the foot back on the insole, so the metatarsal raise stays behind the ball of the foot instead of drifting under it. If you also have flat feet, see our flat feet insoles.
Where should the metatarsal raise sit for Morton’s neuroma?
Just behind the ball of the foot, never under it. In a pressure study using CT scans to confirm exactly where the pad sat, placements about 6 to 11 mm behind the line of the metatarsal heads gave a consistent drop in peak forefoot pressure, averaging 32%. Pads that crept forward past that line made pressure worse (Hastings et al., 2007).
That study was carried out in people with diabetes, not neuromas, but the lesson carries over: a few millimetres decide whether a raise helps or hurts. It is the main reason a loose, stick-on pad is hit-and-miss.
To check your fit, stand in the shoe. You should feel the dome under the soft area behind the ball of your foot, roughly where the forefoot naturally arches. If it feels like a marble under the painful spot, the insole is probably too large or sitting too far forward, so try the next size down or contact us before you give up on it.
Do I need custom orthotics from a pedorthist, or will ready-made insoles work?
For most people, a well-designed ready-made insole is a reasonable first step. The insole that worked in the 2019 trial was made of EVA foam with a metatarsal raise and arch support, which are the same features built into Footlogics forefoot insoles.
Custom orthotics make sense if your foot has a rigid deformity, an unusual shape, or another condition that a standard shape cannot accommodate. In Canada they are made by Canadian Certified Pedorthists (C. Ped (C)), podiatrists or chiropodists, depending on your province, after a hands-on assessment.
If you have already tried a ready-made insole with a correctly placed raise and still have pain, that assessment is worth booking. Ask about extended health coverage first; most group plans only reimburse custom devices with a prescription (more detail in our metatarsalgia insoles FAQ).
How do I fit an insole without crowding my toes?
Make room first: take out the shoe’s original footbed, then put the insole in its place. A shoe that is tight across the forefoot squeezes the metatarsals together and undoes most of what the raise is trying to achieve.
Check the widest part of your foot, not just the length. If the sides of the shoe press on the base of your toes with the insole in, that pair is too narrow, however good the insole is. A wider fit or a rounder toe box usually solves it.
In a Canadian winter, thick socks add more bulk than people expect. Try your boots on with the socks you will actually wear, and if they feel tight, choose a thinner insole or a roomier boot. Our winter boot insoles page has more on fitting.

How long should I try insoles before looking at other options?
Give a correctly fitted insole and roomier shoes a fair trial. In the staged program above, patients moved on to the next stage only if they had not improved enough after three months.
Break new insoles in over the first week, starting with a few hours a day. Mild awareness of the raise is normal; sharper pain, new numbness or a feeling of pressure in the wrong spot is not, so stop and check the size and position.
See a professional sooner if your toes are going numb, the pain wakes you at night, or you have diabetes or poor circulation. In Canada that can be your family doctor, a podiatrist or chiropodist, a physiotherapist or a pedorthist. Our Morton’s neuroma guide covers injections, surgery and other treatments.
Which Footlogics insole is best for my shoes?
Choose by the shoe you wear most, because every model below has the same built-in metatarsal raise. The difference is length, thickness and how much room each needs.
| Insole | Length | Best for | Price (CAD) |
| Footlogics Metatarsalgia | 3/4 | Flats, loafers and casual shoes with little spare room | $34.95 |
| Footlogics Meta Full-length | Full | Lace-up runners, walking shoes, work boots | $37.95 |
| Footlogics 3/4 Meta Pro | 3/4 | Slip-ons; firmer nylon shell for longer life | $39.95 |
| Footlogics Versa | Slim full | Women’s flats, dress shoes and low-heeled boots | $39.95 |
| Footlogics Meta Premium | Full | Lace-ups and winter boots; 12 mm of forefoot cushioning on a nylon shell | $44.95 |
| Footlogics Active | Full | Pickleball and tennis shoes | $44.95 |
Not sure about size? The raise only works in the right place, so check the sizing guide before you order. Free shipping on orders over $60.
FAQs: Insoles and orthotics for Morton’s Neuroma
- Can an insole make Morton’s neuroma worse?
Yes, if the raise sits in the wrong place or the shoe becomes too tight. A raise that lies under the painful spot, rather than behind it, can press on the nerve and increase pressure. An insole that crowds the toe box squeezes the metatarsals together. If pain sharpens or numbness increases after a few days, check the size and the shoe width, and stop wearing that combination until it is sorted.
- Is a “neuroma pad” different from a metatarsal pad?
Mostly in name. Both are domes placed behind the metatarsal heads to spread them and offload the forefoot. Some neuroma pads are narrower and aimed at one gap between two bones, while a metatarsal pad supports the middle of the forefoot more broadly. Either can work if positioned correctly; a raise moulded into a full insole is simply easier to keep in the right spot.
- My neuroma is between my second and third toes. Will the same insole help?
Usually, yes. Most neuromas form between the third and fourth toes, but some develop one space over. A metatarsal raise sits under the middle of the forefoot rather than a single gap, so it offloads both spaces. If your symptoms are clearly on one side and the insole doesn’t help, a pedorthist or podiatrist can add a small targeted pad to it.
- Can I wear insoles after a cortisone injection or neuroma surgery?
After an injection, yes, and many clinicians recommend it, because the shoes and pressure that irritated the nerve are still there once the injection wears off. After surgery, follow your surgeon’s timeline. Insoles normally come back once you are cleared to return to regular shoes, and the forefoot can stay tender for several weeks.
- Can I move one pair of insoles between different shoes?
You can, as long as each shoe has a removable footbed and enough room. Moving a full-length insole between runners and work boots works well. Switching between lace-ups and slim dress shoes rarely does, because one model can’t suit both depths. Most people end up with a full-length pair for everyday shoes and a slimmer pair, such as Versa, for dress or fashion shoes.
- Will insoles help if I stand on concrete all day at work?
They can make a real difference, because hours on hard floors keep load on the forefoot without a break. Pair a full-length insole with a metatarsal raise, such as Meta Full-length or Meta Premium, with a work boot that has a roomy toe box. Steel and composite toe caps can press on the toes, so try boots on with the insole in. See our work boot insoles for more.
References
- de Oliveira HAV, Natour J, Vassalli M, Rosenfeld A, Jennings F, Jones A. Effectiveness of customized insoles in patients with Morton’s neuroma: a randomized, controlled, double-blind clinical trial. Clinical Rehabilitation. 2019;33(12):1898–1907. doi:10.1177/0269215519873949
- Bennett GL, Graham CE, Mauldin DM. Morton’s interdigital neuroma: a comprehensive treatment protocol. Foot & Ankle International. 1995;16(12):760–763. doi:10.1177/107110079501601204
- Saygi B, Yildirim Y, Saygi EK, Kara H, Esemenli T. Morton neuroma: comparative results of two conservative methods. Foot & Ankle International. 2005;26(7):556–559. doi:10.1177/107110070502600711
- Kilmartin TE, Wallace WA. Effect of pronation and supination orthosis on Morton’s neuroma and lower extremity function. Foot & Ankle International. 1994;15(5):256–262. PEDro record
- Hastings MK, Mueller MJ, Pilgram TK, et al. Effect of metatarsal pad placement on plantar pressure in people with diabetes mellitus and peripheral neuropathy. Foot & Ankle International. 2007;28(1):84–88. doi:10.3113/FAI.2007.0015
- Munir U, Tafti D, Morgan S. Morton Neuroma. StatPearls, NCBI Bookshelf. NBK470249
- Study of the anatomical association between Morton’s neuroma and the space inferior to the deep transverse metatarsal ligament using ultrasound. Diagnostics. 2022;12(6):1367. PMC9222077
- Pedorthic Association of Canada. Find a Canadian Certified Pedorthist
